
A clinic can complete regular chair checks and still lose time because nobody owns the service contract, replacement-parts file or handover after a repair. Dental chair maintenance planning is a management task: make responsibilities clear, keep configuration records usable and agree how an issue moves from clinic staff to the supplier and service technician.
This guide is for clinic managers, procurement teams and distributors arranging ongoing support. It covers the maintenance program behind the checklist. For equipment checks and fault escalation, use the dental chair maintenance checklist. Exact service procedures and intervals must come from current model instructions and appropriately qualified personnel.
Begin with a usable equipment register
Create a record for each chair rather than one generic entry for the clinic. Include the model, serial number, room, installation date, supplier, configuration revision and separately supplied accessories. Attach the current manual, approved installation documents and commissioning record. Identify who updates the register when a component is replaced or the chair moves to another room.
The register should distinguish the chair from shared systems such as the compressor and suction plant. A problem reported at one dental unit may need investigation elsewhere, and each asset may have a different contractor or service agreement. Cross-reference the equipment without assuming that the chair warranty covers the entire installation.
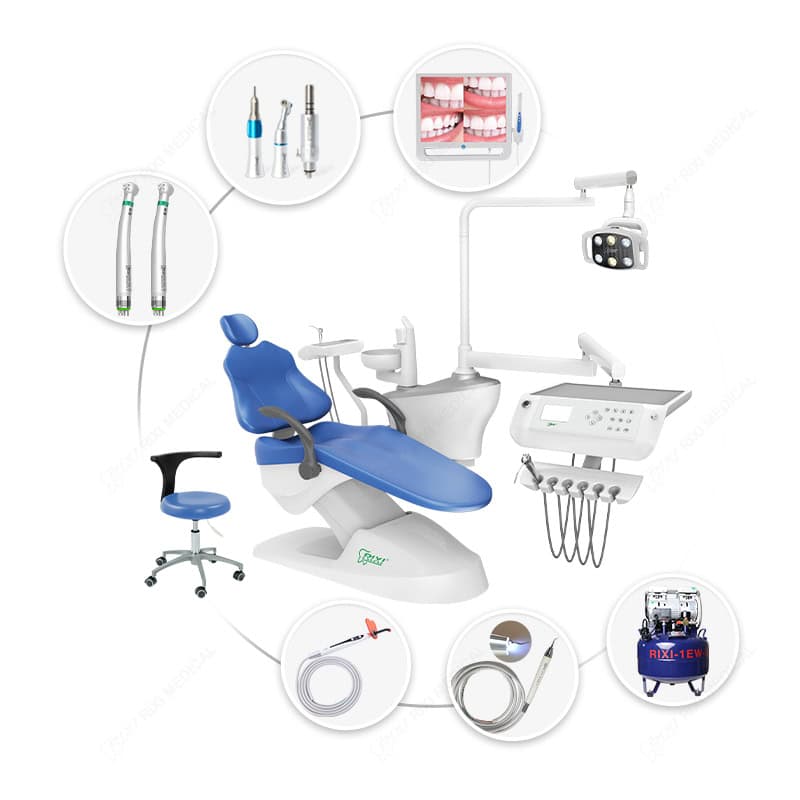
Define the service scope before comparing prices
Ask potential service providers to describe what they inspect, what they adjust and which work requires separate authorization. Separate routine visits, fault diagnosis, emergency callouts, replacement components, travel and post-service testing. Confirm whether the provider covers the supplied accessories and shared utilities or only the chair mechanism.
A lower quoted visit fee may exclude components or labor that another proposal includes. Normalize the scope first and record exclusions. Ask whether supplier-specific training or documentation is needed for the work and who obtains it. The installation requirements guide helps identify responsibilities that should have been established at commissioning.
Assign ownership without turning staff into technicians
Name a clinic coordinator who holds the current documents and contacts the service provider. Identify trained staff responsible for permitted routine checks. Internal electrical, hydraulic or structural work belongs with appropriately qualified technicians, using the exact model instructions.
Agree who decides whether equipment should be removed from service, who provides an alternative room and who communicates the operational change to staff. A clear escalation route is useful even when a clinic has only one chair. Avoid expecting the first person noticing a fault to choose a replacement part or diagnose the cause.
| Responsibility | Owner to name | Record needed |
|---|---|---|
| Document control | Clinic equipment coordinator | Current manuals and configuration register |
| Routine operator tasks | Trained staff assigned by the clinic | Permitted-task instructions and completion record |
| Technical diagnosis | Qualified service provider | Fault report and diagnostic findings |
| Parts approval | Supplier and purchasing contact | Compatible identifier and quotation |
| Return to service | Technician and clinic representative | Required tests and resolved outstanding points |
Set visit timing from the model and operating context
Use the manufacturer’s stated service requirements as the starting point. Ask the service provider how usage, environment, previous faults and installed options affect the program. Do not promise a universal annual interval or guaranteed chair lifespan. Where no interval is available, request clarification from the equipment supplier.
Schedule visits around realistic room availability and confirm access to isolation points, removable covers and utilities. Tell the provider which faults are unresolved before the visit so necessary documents and parts can be considered. For unfamiliar configurations, request an access review rather than assuming technicians can reach every component after cabinetry is installed.
Prepare parts and budget information that can be used
A spare-parts plan should list supplier identifiers, compatible model revisions, storage instructions and the person authorized to order. Ask which parts are appropriate to hold locally and which should be supplied after diagnosis. Inventory is only useful if the parts match the chair and remain suitable under their storage requirements.
The dental accessories category can frame a supplier discussion, but a catalog photograph does not establish compatibility. Confirm identifiers and revisions before purchasing. Record installation labor, shipping and any other charges separately from the component price so the clinic can compare a complete quotation.
Keep actual service invoices and interruption records. They can inform the clinic’s budget and replacement decisions; they should not be converted into a universal return-on-investment figure or a promised saving for another clinic. Compare recurring faults with technical findings before deciding between repair, replacement or changes to supporting utilities.
Close each service visit with a handover record
Request a report identifying the equipment, reported symptoms, findings, work performed, parts used and checks required by the model procedure. List unresolved items and who owns the next action. If the provider changes a setting or replaces a component, update the register and retain the applicable document revision.
Confirm the conditions for returning the unit to service with the technician and clinic’s responsible representative. A completed invoice does not explain whether all reported issues were resolved. Use an acceptance record that distinguishes completed work from pending approval or additional investigation.
Distributor support across several clinics
Distributors should keep a configuration register by customer and shipment, including accessory changes and replacement-part history. Assign a route for obtaining model documents, escalating faults and confirming compatible replacements. Agree how customers receive revision notices and whether a local service provider or supplier handles each support stage.
Use RIXI technical support to request current technical information, while putting purchase-specific support terms in the written agreement. Do not infer local service coverage, response guarantees or warranty exclusions from a general website statement.
Frequently asked questions
What belongs in a maintenance agreement?
Identify covered assets, included tasks, exclusions, responsibility for parts, access requirements, escalation contacts and the records delivered after service.
Does a service visit automatically preserve warranty coverage?
Check the written warranty for the exact purchase. Keep relevant records and request clarification about required service or permitted work.
Should the clinic stock every replacement part?
No. Agree a practical list with the supplier and technician based on compatibility, storage conditions and support arrangements.
How can a distributor manage repeat configurations?
Track model and accessory revisions, parts identifiers and document changes by shipment. Notify the receiving clinic when its support instructions change.
Scope: Maintenance program ownership, purchasing and documentation. It does not prescribe repair methods or service intervals.
To define a support program, contact RIXI Medical with the equipment register, destination and proposed responsibilities.
Need Dental Equipment Pricing or Configuration Details?
Contact RIXI Medical for model comparison, distributor pricing, packaging information, OEM/ODM requirements and after-sales support.
Request Product Information

